
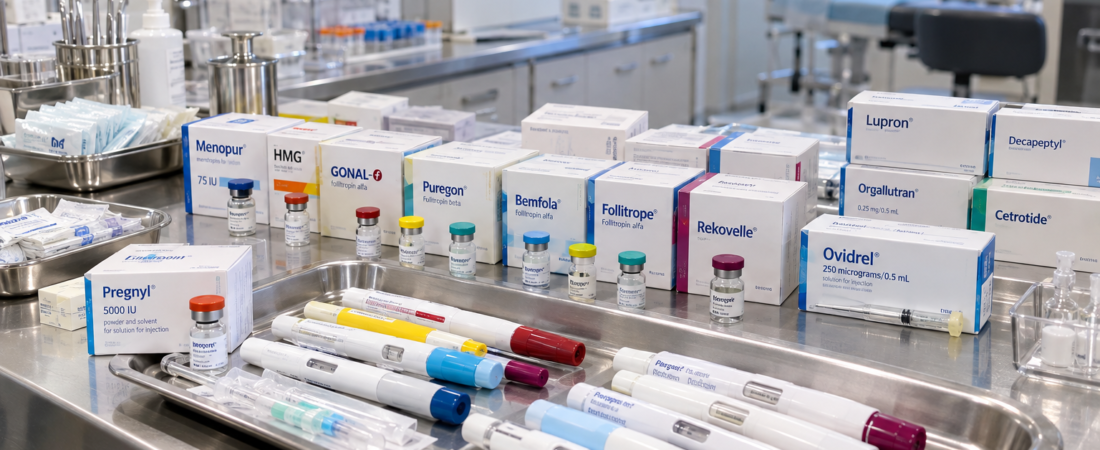
Why can the same IVF stimulation injections yield 15 eggs for one patient and 3 for another? Ovarian reserve, the starting follicle count, medication and protocol all matter. Higher doses or adding LH do not automatically improve live birth, and treatment must balance egg yield with the risk of ovarian hyperstimulation syndrome (OHSS).
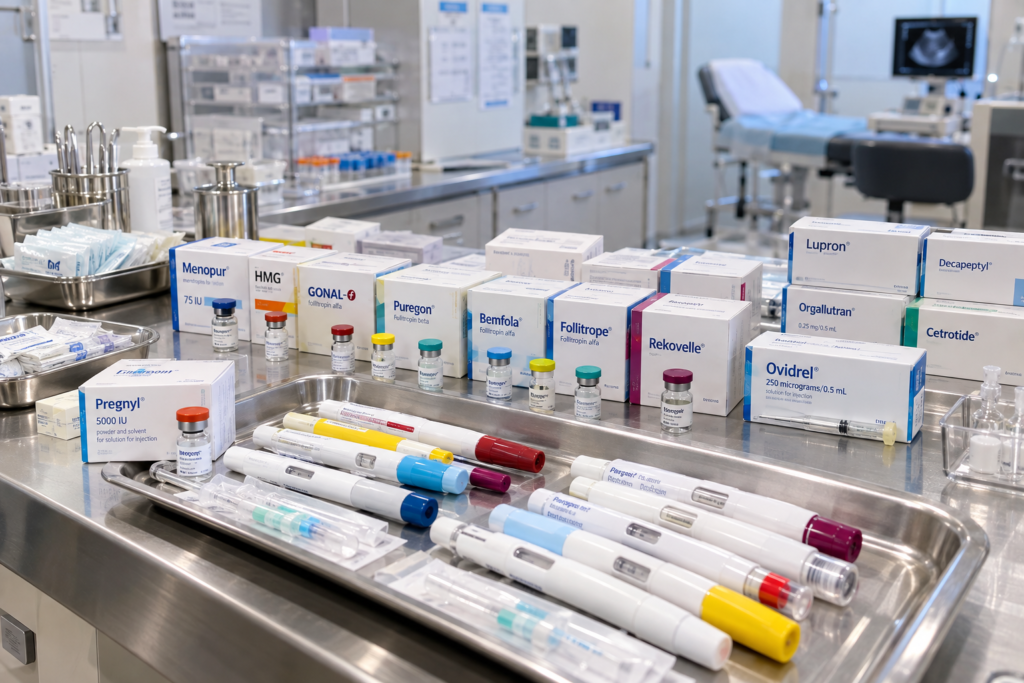
“The Same Stimulation Injections, Yet Why 15 Eggs for One and 3 for Another?”
- FSH alone, LH-supplemented, and hMG formulations: Active biological ingredients diverge, and individual ovarian responsiveness varies widely
- A shifting paradigm in reproductive medicine: Moving away from “maximal gonadotropin dosing” toward precision stimulation tailored to individual ovarian biology
- Limits to increasing the FSH dose: More medication does not guarantee more eggs or a live birth; lower starting doses may reduce excessive response in predicted high responders, but do not eliminate OHSS
When starting In Vitro Fertilization (IVF), nearly every woman becomes intimately familiar with ovarian stimulation injections. Administering a shot into the abdomen at the exact same hour each evening, she returns to the clinic days later to watch dark, circular follicles appear across the ultrasound monitor.
Yet even when patients begin treatment at the exact same clinic during the exact same week, the outcomes diverge dramatically.
One woman recruits more than ten growing follicles, while another sees only two or three. In other instances, a woman who showed a lackluster response in her prior cycle switches medications and suddenly recruits a substantially larger cohort of eggs. Fertility forums are filled with recurring questions and personal anecdotes: “This specific injection didn’t work for my body,” or “Switching to that other brand gave me so many more eggs.”
Does the human body truly respond differently to different stimulation medications? The short answer is yes. The explanation is straightforward: ovarian stimulation injections do not all share the same active ingredients, and no two ovaries interpret those hormonal signals in the exact same way.
How Does FSH Help Multiple Follicles Grow?
In an unmedicated menstrual cycle, a cohort of small antral follicles begins growing in the early follicular phase, but natural physiological feedback ensures that only one dominant follicle is selected for ovulation, while the remaining follicles undergo atresia and die off.
Because assisted reproduction requires securing multiple oocytes to produce viable embryos, this natural selection process must be pharmacologically overridden. Exogenous Follicle-Stimulating Hormone (FSH) is administered to support several follicles that might otherwise stop developing, allowing multiple follicles to mature in parallel; not every recruited follicle will respond or yield an egg.
Consequently, the core driver in the vast majority of stimulation medications is FSH. However, formulation differences begin immediately:
- Some medications deliver recombinant FSH alone.
- Some combine FSH with Luteinizing Hormone (LH) bioactivity.
- Some are purified from the urine of postmenopausal women, while others are bioengineered using recombinant DNA technology.
While they are all broadly categorized as “ovarian stimulation shots,” the precise molecular dialogue they establish with the ovary varies.
What Does LH Add to Ovarian Stimulation?
FSH acts directly on granulosa cells to power follicular expansion. Why, then, would an injection need LH?
Within the developing follicle, multiple cell types cooperate through continuous biochemical crosstalk—a process governed by the classic two-cell, two-gonadotropin model:
- Theca Cells & LH: Circulating LH binds to LH receptors on outer theca cells, stimulating the enzymatic conversion of cholesterol into androgens (such as androstenedione and testosterone).
- Granulosa Cells & FSH: These androgens diffuse across the basement membrane into adjacent granulosa cells, where FSH activates the aromatase enzyme to convert those androgens into estradiol (estrogen).
Put simply, LH provides the raw biochemical substrates, while FSH utilizes those substrates to drive follicular growth.
However, this does not mean an injection with high LH activity is universally superior. Many women—particularly younger patients with robust baseline ovarian reserve—produce sufficient endogenous LH and respond excellently to pure FSH alone.
LH replacement has an established role in severe FSH and LH deficiency. For the general IVF population, low responders and women aged 35 or older, ESHRE gives similar conditional recommendations for recombinant FSH alone and recombinant FSH plus LH; a clear live-birth advantage from adding LH has not been established. Receptor variants are being studied, but they do not establish that adding LH routinely improves follicular synchrony.
Modern reproductive endocrinology has largely moved past debating “Is LH good or bad?” to focus on “Which specific patient phenotype genuinely benefits from LH supplementation?”
How Does hMG Differ from Recombinant FSH and LH?
A mainstay in ovarian stimulation protocols is Human Menopausal Gonadotropin (hMG).
Clinicians and patients often refer to hMG as a combined “FSH + LH injection.” More precisely, it is a medication that delivers both follicle-stimulating and luteinizing bioactivity:
- The hCG Mechanism in hMG: Menopur provides both FSH and LH bioactivity. Most of its LH bioactivity comes from human chorionic gonadotropin (hCG), with a smaller contribution from LH. The current UK product information states that hCG from pregnant women’s urine may be added to achieve the required LH bioactivity. hCG acts at the shared LH/hCG receptor.
- Recombinant Co-Formulations: In contrast, dual-recombinant medications (such as Pergoveris) deliver bioengineered recombinant human LH (r-hLH) paired directly with recombinant human FSH (r-hFSH) in a precise fixed ratio.
For patients, both strategies serve the same functional purpose: pairing the primary follicular growth stimulus of FSH with supporting LH bioactivity.
“I Switched Injections and Got More Eggs”… Was It Really the Medication?
Consider an illustrative example: a woman uses recombinant FSH in her first cycle and retrieves only 3 eggs; in her next cycle, her physician switches her to an hMG-containing regimen, and she retrieves 8. This is a scenario, not the result of a cited head-to-head trial.
While pharmacological differences between medications can certainly influence follicular recruitment, it is difficult to attribute that change entirely to the drug.
The human ovary is not biologically identical from one month to the next.
The antral follicle count can vary between assessments, although AMH and AFC are relatively consistent reserve markers. Age, the measured baseline follicle count, hormone measurements and the protocol help clinicians interpret the starting point. Hormonal contraceptives can suppress AMH and AFC measurements; a difference between two cycles cannot by itself prove that a particular drug brand caused the change.
While switching medications may have played a constructive role, the ovary’s biological starting point that particular month may simply have been far more receptive.
What Does the Evidence Show for hMG vs. Recombinant FSH?
What do large-scale trials demonstrate when comparing these formulations head-to-head?
The 2026 Cochrane update included 59 randomized controlled trials involving 18,119 women across several gonadotropin comparisons. Not all 59 trials compared recombinant FSH directly with urinary hMG or highly purified hMG (HP-hMG):
- For the rFSH versus HMG/HP-hMG comparison, the review concludes that rFSH probably yields lower live-birth and clinical-pregnancy rates and higher OHSS rates. This is the conclusion for that comparison, not for every gonadotropin preparation or treatment protocol.
- However, this cannot be translated into a blanket clinical rule that “hMG is superior for every woman.” The included trials spanned diverse patient demographics, baseline ovarian reserves, and protocol designs.
Above all, raw egg counts alone do not determine clinical success. A retrieval of 20 oocytes may still produce few usable embryos, while 6 mature eggs may lead to a live birth. These are possibilities, not evidence that fewer eggs are better or that higher counts cause post-maturity. Egg number alone cannot establish embryo chromosomal status or guarantee a healthy baby.
Does a Higher FSH Dose Guarantee More Eggs?
When starting a cycle, patients often become preoccupied with daily dosages. Prescriptions range from 150 IU to 225 IU, 300 IU, or even 450 IU daily, sparking the intuitive belief: “If we push the dose higher, won’t my ovaries produce more eggs?”
The ovary does not function like an open water faucet where turning the handle further produces an endless stream of eggs.
A 2026 conference abstract reported a single-center, open-label randomized trial in 182 predicted normal responders. Starting recombinant FSH at 225 IU rather than 150 IU did not show a statistically significant increase in retrieved oocytes or cumulative live births. The trial was small, allowed later dose adjustments and does not establish the best dose for every patient.
The FSH ceiling effect is a shorthand for the limited benefit that further dose increases may provide, not a precisely measurable point at which every patient’s receptors become saturated. ESHRE treats 150–225 IU as a conventional dose range for predicted normal responders and does not recommend doses above 300 IU for predicted low responders. Dose selection remains a clinical decision.
In fertility medicine, “administering more medication” is not synonymous with “stimulating the ovary better.”
Why May High AMH Call for a Lower Starting Dose?
Certain patient cohorts require deliberate restraint—most notably women with elevated AMH levels or Polycystic Ovary Syndrome (PCOS).
Anti-Mullerian Hormone (AMH) helps predict ovarian response. High values can indicate a larger responding follicle cohort and greater risk of excessive response and Ovarian Hyperstimulation Syndrome (OHSS). AMH is not a direct measurement of egg quality, and a high result does not mean that every follicle will respond.
To navigate this, modern protocols increasingly utilize personalized dosing algorithms calculated from baseline AMH and body weight prior to cycle start. A prime example is follitropin delta.
In the 1,329-woman ESTHER-1 randomized trial, AMH- and weight-based follitropin delta was noninferior to conventional follitropin alfa for the primary ongoing-pregnancy and ongoing-implantation outcomes; live-birth rates were similar. Excessive ovarian responses and the need for OHSS preventive measures were reduced. OHSS alone was not significantly different (3.5% versus 4.8%; P=0.238), whereas the combined outcome of OHSS and/or preventive intervention was lower. This distinction matters when discussing safety.
For predicted high responders, ESHRE conditionally recommends a lower starting gonadotropin dose to reduce OHSS risk. The dose is only one part of prevention; the stimulation protocol, trigger and transfer strategy also matter. Patients should not change their prescribed dose themselves.
Is There One Ideal Number of Eggs?
Every woman undergoing egg retrieval wonders: “How many eggs will we get?”
While patients understandably focus on egg numbers, the answer depends on age, ovarian response, safety and the outcome being measured. A live birth after a fresh transfer and a cumulative live birth after using fresh and frozen embryos are different endpoints.
The 8 to 14 retrieved oocytes range was the prespecified target response in ESTHER-1, not a universal peak for cumulative live birth. A later pooled analysis of four follitropin-delta trials found that one-year cumulative live birth could continue to increase at higher egg yields, with patterns differing by age. That association does not prove that increasing medication to obtain more eggs improves outcomes; excessive response still raises safety concerns.
Consequently, modern reproductive medicine has shifted away from historical “collect as many as possible” strategies toward securing a safe, developmentally competent cohort of mature eggs capable of yielding healthy blastocysts.
Why Do Two Women with the Same AMH Yield Different Egg Counts?
This remains a frequent source of frustration for patients. A woman compares notes with a friend of identical AMH: one retrieves 10 eggs, while the other retrieves only 3.
AMH is produced by small growing follicles and serves as an indirect marker of ovarian reserve and likely response. It does not count the remaining primordial follicles directly, measure egg quality, or forecast the exact number of eggs retrieved in a particular cycle.
Clinical response reflects several factors, while some proposed biological contributors remain under investigation:
- Chronological age and baseline Antral Follicle Count (AFC)
- Body mass index (BMI) and pharmacological volume of distribution
- Genetic variations (polymorphisms) in the FSH receptor (FSHR) and LH receptor (LHCGR), which are being investigated rather than established as routine guides to choosing stimulation drugs
- The follicular androgen environment, a biological contributor under investigation rather than a routine test that predicts an individual egg count
- The specific stimulation protocol, starting day, and gonadotropin formulation
This complexity helps explain why responses can differ. A change from 3 eggs in one cycle to 7 in another is an illustration of variability, not proof of one mechanism or a guarantee that switching medication will help.
What Can the First Stimulation Cycle Tell Your Clinician?
When an initial IVF cycle yields fewer eggs than anticipated, patients understandably feel devastated, often interpreting the outcome as an absolute failure.
From a clinical perspective, that first stimulation provides observed response data that complements blood tests and ultrasound:
- How did follicles grow at the doses that were used?
- Did the follicular cohort develop synchronously, or was growth uneven?
- What percentage of retrieved eggs reached Metaphase II (MII) maturity?
- How did fertilization and blastocyst conversion progress?
Using these physiological insights, the reproductive endocrinologist can adjust the strategy for the subsequent cycle: refining starting doses, introducing LH bioactivity, incorporating hMG, or altering the ovulation trigger.
A first retrieval is not merely an attempt to secure oocytes; it is the process of deciphering how a woman’s unique ovaries respond to hormonal stimulation.

How Are IVF Stimulation Medications Classified?
The commercial names for stimulation medications can be overwhelming, but memorizing individual brands is unnecessary. Grouping them by their active endocrine mechanisms clarifies why prescription changes are made:
| Medication Category | Common Examples | Biological Mechanism & Clinical Rationale |
| Recombinant FSH Monotherapy | Gonal-F, Puregon, Rekovelle (follitropin alfa, beta, delta) | Pure FSH receptor stimulation; drives granulosa cell proliferation and follicle growth without added LH activity |
| Dual Recombinant FSH + LH | Pergoveris (follitropin alfa + lutropin alfa) | Fixed-ratio recombinant FSH and LH (2:1); the EU indication is follicular development in adult women with severe FSH and LH deficiency |
| Human Menopausal Gonadotropin (hMG) | Menopur (highly purified hMG) | Urine-derived gonadotropins providing FSH and LH bioactivity; hCG supplies most of the LH bioactivity |
| Long-Acting Recombinant FSH | Elonva (corifollitropin alfa) | Long-acting recombinant FSH modified with an hCG-derived peptide; one injection can replace the first seven daily FSH injections in the indicated regimen. It has no intrinsic LH/hCG activity |
Understanding these categories helps explain why a physician may modify a prescription. The aim is to tailor treatment using the previous response, safety considerations and clinical evidence. Adding LH or hMG does not guarantee a better outcome; ESHRE does not recommend rFSH plus hMG over either alone for normal or low responders.
What Should Patients Take Away?
In ovarian stimulation, there is no single “best injection” that works universally for every human body.
Success does not lie in choosing the most aggressive or expensive medication on the shelf, but in understanding how a patient’s individual ovarian physiology behaves under stimulation.
The journey through IVF can involve refining the formulation, dose and protocol using the response observed so far. The goal is a safe, effective treatment plan, with realistic expectations about what changes can and cannot achieve.
※ This article was synthesized based on the “Ovarian Stimulation for IVF/ICSI” clinical practice guidelines published by the European Society of Human Reproduction and Embryology (ESHRE) alongside practice committee documents and gonadotropin literature from the American Society for Reproductive Medicine (ASRM) and the Cochrane Collaboration. It does not replace individualized clinical diagnosis or medical care, and specific treatment decisions should always be made in consultation with a qualified reproductive endocrinologist.
※ The images associated with this article were generated using generative AI (ChatGPT, OpenAI) as illustrative visual references and do not depict real individuals.
Related reading: rFSH alone versus rFSH plus HP-hMG in real-world IVF care examines an observational study and explains why treatment-group differences do not establish which regimen is better.
Sources and Further Reading
- ESHRE ovarian stimulation guideline, 2025 update (September 2026 version)
- ASRM: Testing and interpreting measures of ovarian reserve (2020)
- ASRM: Hormonal contraceptives in fertility treatment (2024)
- Cochrane gonadotropin review update (August 2026)
- Zhang et al., 150 IU versus 225 IU randomized trial, 2026 conference abstract
- ESTHER-1 randomized trial, Fertility and Sterility (2017)
- Lobo et al., one-year cumulative live birth and oocyte number, Human Reproduction (2025)
- Menopur UK product information
- Pergoveris EU product information
- Elonva EU product information
- GONAL-f UK product information
- Exploratory LHCGR genotype study (2021)