
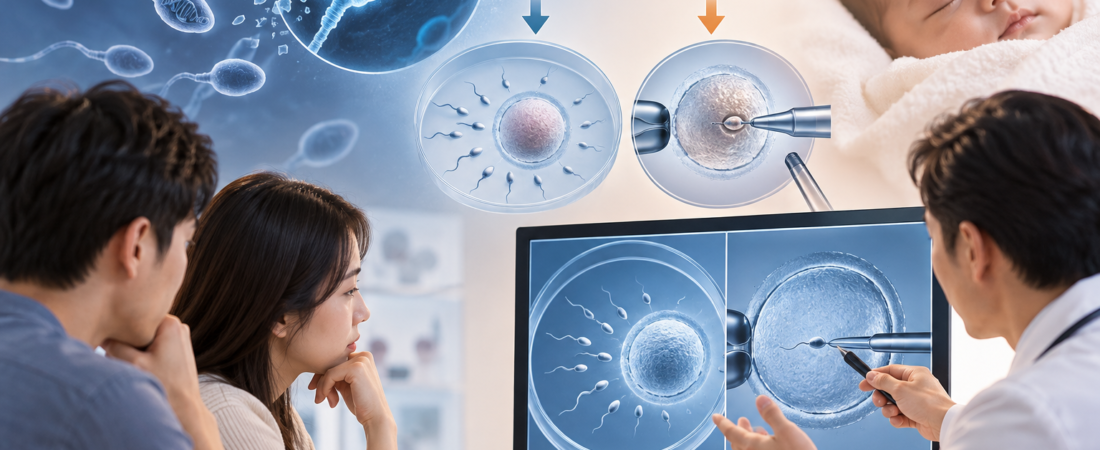

- Comparing cumulative live birth rates between IVF and ICSI in couples without severe male factor infertility
- In standard IVF, live birth probability declined as DFI increased; in ICSI, no clear negative association was observed
- An inflection point observed around a DFI of ~14%… “Not a rigid, universal threshold for ICSI”
“Our sperm count and motility look acceptable, but the DNA fragmentation rate came back elevated. Should we jump straight to intracytoplasmic sperm injection (ICSI) from the start?”
This is a recurring dilemma for couples navigating assisted reproductive technology. A routine semen analysis evaluates parameters like total concentration, progressive motility, and normal morphology. However, even if these conventional metrics fall within reference ranges, they cannot guarantee the genomic integrity of the DNA packaged inside the sperm head.
Recent clinical research demonstrates that this metric—the sperm DNA fragmentation index (DFI)—can exert distinct effects on live birth outcomes depending on whether a couple undergoes standard in vitro fertilization (IVF) or ICSI.
Analyzing couples without severe male factor infertility, researchers observed that in conventional IVF, higher rates of sperm DNA damage correlated with a steady decline in cumulative live birth rates (CLBR). In contrast, among couples undergoing ICSI—where an individual sperm is microinjected directly into an oocyte—this negative correlation was largely attenuated.
DFI Measures What Routine Semen Analysis Misses
DFI stands for the DNA Fragmentation Index, representing the percentage of spermatozoa exhibiting broken, fragmented, or damaged DNA strands.
Under a light microscope, a sperm cell can possess normal morphology and vigorous forward motility while harboring significant single- or double-strand DNA breaks within its nucleus. Conversely, a semen sample displaying mildly reduced count or motility does not automatically mean that every sperm carries fragmented DNA.
For this reason, a DFI assay provides complementary biological insight beyond conventional semen parameters.
Investigators from the Center for Reproductive Medicine at Chenggong Hospital, affiliated with Xiamen University School of Medicine, noted that standard semen analysis alone is insufficient to fully characterize male reproductive competence. In their study, they evaluated whether DFI could serve as a clinical decision-making biomarker to help determine whether standard IVF or ICSI is more appropriate in patients who do not present with severe male factor infertility.
Balancing Cohorts: IVF and ICSI Outcomes Diverge Under Propensity Score Matching
The researchers measured DFI using the Sperm Chromatin Structure Assay (SCSA) and evaluated reproductive outcomes following IVF and ICSI.
In retrospective real-world data, the baseline characteristics between IVF and ICSI cohorts are rarely identical; for example, clinicians are far more likely to select ICSI for patients with poorer sperm profiles, introducing selection bias. To control for these baseline disparities, the investigators performed rigorous propensity score matching (PSM), establishing two well-balanced cohorts: 398 IVF cycles matched against 398 ICSI cycles.
The findings revealed divergent clinical trajectories:
- Standard IVF: Cumulative live birth rates declined progressively as the sperm DFI rose.
- ICSI: No statistically significant correlation was detected between DFI levels and cumulative live birth rates.
Here, cumulative live birth rate (CLBR) does not simply track whether a single embryo transfer succeeded; it evaluates the likelihood of taking home a baby from all fresh and frozen embryo transfers derived from a single complete oocyte retrieval cycle. It reflects the ultimate clinical objective of fertility treatment.
When DFI Was Low, Standard IVF Showed Superior Outcomes
What drew particular clinical interest was that the relative advantage between the two fertilization techniques shifted depending on the baseline DFI level.
In the investigators’ statistical models, when the DFI fell below approximately 14.3%, the cumulative live birth rate for standard IVF trended higher than that of ICSI.
As DFI increased, however, outcomes for standard IVF steadily declined. In an alternate non-linear regression model, standard IVF retained a relative advantage at DFI levels below 14.2%, but once fragmentation exceeded this threshold, ICSI yielded comparatively better outcomes.
In practical terms, this suggests that routinely defaulting to ICSI for men with minimal or low sperm DNA damage does not inherently confer a reproductive advantage—and may even yield lower cumulative outcomes than allowing natural fertilization in vitro.
Conversely, when sperm DNA fragmentation is elevated, the physiological barriers of standard IVF—such as penetration through the cumulus complex and the zona pellucida—may be insufficient to filter out spermatozoa carrying compromised chromatin. Under ICSI, where clinical embryologists manually select individual spermatozoa exhibiting optimal motility and morphology at high magnification, the negative impact of higher background DFI appears relatively buffered.
However, this does not mean that ICSI physically “repairs” fragmented DNA. If a sperm carrying damaged DNA is inadvertently injected, ICSI cannot undo that genetic burden.
Why ‘14%’ Should Not Be Treated as a Dogmatic Cutoff
The most critical figure requiring cautious interpretation is the 14% threshold.
Taking these findings at face value might tempt clinicians and patients to adopt a rigid clinical formula: “DFI under 14% means standard IVF, and DFI over 14% mandates ICSI.” Such an interpretation is clinically flawed.
The 14.2%–14.3% cutoff represented an inflection point identified within statistical models specific to this single study cohort. It cannot be viewed as a universally validated clinical threshold across all laboratories and patient populations.
DFI values vary considerably depending on the specific testing methodology employed (such as SCSA, TUNEL, SCD, or Comet assays). Furthermore, intra-individual biological variability is well documented: a single individual’s DFI can fluctuate over time based on ejaculatory abstinence intervals, recent febrile episodes, local infections, smoking, oxidative stress, and lifestyle factors.
Indeed, other published literature has evaluated different clinical thresholds, such as a DFI of 20% or 30%. In an earlier large-scale study of 2,713 couples, patients with elevated DFI who underwent conventional IVF demonstrated reduced cumulative live birth rates, whereas ICSI outcomes remained relatively resilient to variations in DFI.
Rather than fixating dogmatically on whether a number is strictly above or below 14%, treatment decisions must integrate sperm concentration, progressive motility, morphology, prior fertilization failure, maternal age, and oocyte yield.
ICSI Is Not an Automatic Cure-All for Every Case of DNA Damage
The overarching takeaway from this research is far from an endorsement that “more ICSI automatically yields higher success rates.”
ICSI remains an indispensable, frontline treatment for severe male factor infertility (such as severe oligoasthenoteratozoospermia, obstructive or non-obstructive azoospermia requiring surgical retrieval) and documented total fertilization failure in previous cycles. However, whether ICSI should be universally applied to couples presenting without severe male factor infertility remains a subject of ongoing debate.
A 2026 secondary analysis of a randomized clinical trial showed that routine DFI screening in non-severe male factor couples had limited utility in definitively isolating which patients would derive a decisive therapeutic benefit from ICSI over IVF.
The study from Xiamen University is a retrospective cohort analysis utilizing matched pairs; it is not a prospective randomized controlled trial proving causality.
Ultimately, the takeaway is not that “fragmented DNA mandates ICSI by default.” Rather, in cases of unexplained infertility, recurrent embryo arrest, or repeated implantation failures where conventional semen parameters appear ostensibly normal, a high DFI serves as an additional diagnostic datapoint—helping clinicians weigh whether shifting from standard IVF to ICSI offers a justifiable physiological advantage.
Medical Source & Study Reference
- Journal: Andrology (Published online July 28, 2026).
- Study Title: Differential Effects of Sperm Deoxyribonucleic Acid Fragmentation Index on Cumulative Live Birth Rate per Complete Cycle Following IVF and ICSI Treatment in Patients Without Severe Male Infertility
- Lead Institutions: Center for Reproductive Medicine, Chenggong Hospital Affiliated to Xiamen University; School of Medicine, Xiamen University, Xiamen, China.
- Methodology: Retrospective cohort study analyzing 398 IVF cycles matched to 398 ICSI cycles via Propensity Score Matching (PSM).
※ This article provides general medical information and does not replace individualized clinical diagnosis or medical care. Specific treatment plans and choices between IVF and ICSI should always be made in consultation with a qualified reproductive endocrinologist or urologist.
※ The images associated with this article were generated using generative AI (ChatGPT, OpenAI) as illustrative visual references and do not depict real individuals.