
Intralipid Infusions: Prescriptions Outpace Scientific Evidence Soybean oil-based lipid emulsions, originally nutritional IVs, spread through fertility clinics fueled by ‘immunomodulatory potential’ While some studies showed increased pregnancy rates, live birth benefits remain unproven; international societies repeatedly issue non-recommendations Over half of domestic specialists have prescription experience; “hope it might help” must not replace clinical evidence
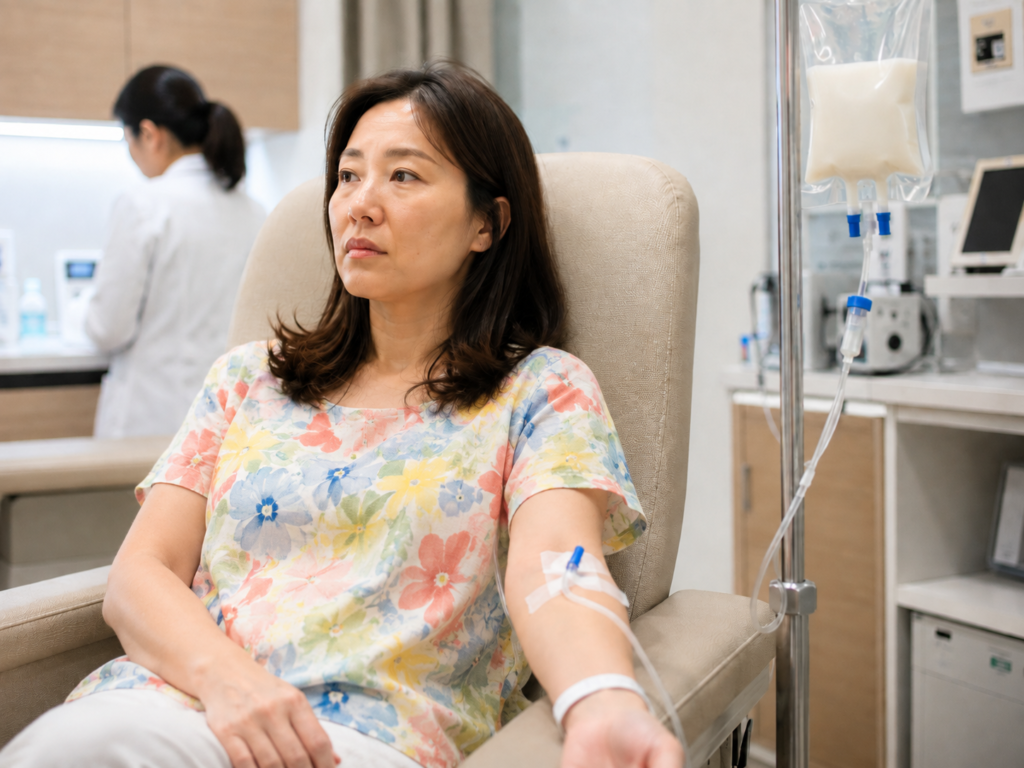
Ahead of an embryo transfer, an infertile woman’s arm is hooked up to a milky-white bag of intravenous fluid. Among fertility patients, it is commonly known as the ‘soybean injection.’
“It lowers immunity to aid implantation.” “It can help reduce recurrent implantation failure or miscarriages.”
For a patient who has already experienced multiple failed transfers, hearing that there is “even the slightest chance” is enough to tug at the heartstrings. However, looking closer at the true identity of this injection reveals a slightly different picture.
The formal name of the ‘soybean injection’ is Intralipid. It was never originally developed for fertility treatments. It is an intravenous lipid emulsion primarily composed of soybean oil, designed to provide calories and essential fatty acids to patients who cannot consume adequate nutrition orally.
Representative 20% formulations contain soybean oil, egg yolk phospholipids, and glycerin. Because of the slow drip of a white, opaque liquid into the veins, fertility patients gave it the nickname ‘soybean infusion.’ Neither infertility nor implantation improvement are originally approved indications.
How a Nutritional Fluid Became an ‘Implantation Adjunct’
The starting point was immunity. Implantation is not merely a process of an embryo sticking to the uterine wall; it is a complex interaction involving the embryo, the endometrium, and the maternal immune system. As the possibility that abnormal immune responses are involved in some patients with recurrent implantation failure and recurrent miscarriages gained traction, immune cells—particularly natural killer cells, known as NK cells—emerged as subjects of research.
Intralipid also drew attention during this process.
Some experiments and early clinical studies suggested that lipid emulsions can suppress NK cell activity and influence inflammation-related signaling molecules such as IL-2, TNF-α, and IL-1β.
Compared to expensive intravenous immunoglobulins (IVIG), Intralipid carried a relatively low financial burden and was already a familiar nutritional fluid in hospitals, lowering the barrier to its widespread prescription. The research finding that it “may modulate immunity” combined with the clinical expectation that it “might help with implantation,” cementing its place as an adjuvant fertility treatment.
The Missing Link: From Pregnancy to Live Birth
This is precisely where the medical controversy begins. A change in NK cell counts is distinct from an increase in actual pregnancies, and an increase in pregnancies is likewise entirely different from a higher rate of delivering a healthy baby.
The most critical outcome in fertility treatment is not two lines on a pregnancy test, but a live birth. Even if a pregnancy is confirmed, it can lead to a miscarriage, meaning treatments must ultimately be evaluated on whether they lead to a healthy delivery. Yet Intralipid has not yet provided a definitive answer at this final hurdle.
This limitation was reaffirmed in a study released on the 10th by the National Evidence-based Healthcare Collaborating Agency (NECA), titled “Evidence-Generation Research for the Appropriate Use of Intralipid Injections for Pregnancy Purposes.”
Analyzing 11 international clinical practice guidelines published over the past decade, NECA found that 7 guidelines concluded Intralipid use lacks sufficient evidence or should not be recommended. The more recent the guideline, the clearer the non-recommendation stance.
Research results likewise did not point in a single direction.
While some randomized controlled trials showed higher clinical pregnancy rates among patients administered Intralipid, the study sizes were small and the level of evidence was low.
Conversely, non-randomized studies even reported higher miscarriage rates in the treatment group. The lack of standardization regarding which patients should receive it, at what timing, and in what dosage if it is effective also remains a major problem.
Stance of International Academic Societies
International societies have reached similar conclusions.
The European Society of Human Reproduction and Embryology (ESHRE) reviewed studies suggesting that Intralipid administration in recurrent implantation failure patients increased pregnancy or live birth rates, but refrained from recommending intravenous Intralipid due to small study sizes and heterogeneous patient cohorts and administration protocols.
The fact that it was frequently used empirically for repeat-failure patients rather than selecting and treating patients with clearly confirmed immunological causes further diminishes the reliability of the evidence.
Safety cannot simply be dismissed with the assumption that “it’s just a nutritional fluid, so it’s fine.”
Intralipid is not food or a dietary supplement; it is a pharmaceutical product administered directly into the veins. Patients with severe allergies to soy, eggs, or peanuts require caution, and it must be used prudently in those with hyperlipidemia, lipid metabolism disorders, or severe liver disease. Though rare, side effects such as liver dysfunction, thrombocytopenia, and fat overload syndrome have been documented during lipid emulsion use.
Intralipid vs. IVIG: Different Drugs, Similar Intentions
Another name fertility patients frequently hear alongside Intralipid is immunoglobulin, or IVIG. However, the two injections are entirely different drugs. IVIG is a blood product administered intravenously, consisting of IgG antibodies purified from the plasma of multiple donors, used for neutralizing autoantibodies and regulating immune cells.
Conversely, Intralipid is a lipid emulsion centered on soybean oil. Their mechanisms and components differ completely. They share only the commonality that both treatments have been attempted for ‘immunomodulation’ in recurrent implantation failure or recurrent miscarriages.
While some studies have also suggested potential efficacy for IVIG, a lack of sufficient randomized trials and risks of side effects—such as thromboembolism, hemolysis, renal abnormalities, and allergic reactions—prevent international societies from recommending it as a routine fertility adjunct. Consequently, Intralipid cannot be oversimplified as an “equally effective alternative” merely because it is cheaper and more familiar than IVIG.
Reality in Domestic Clinical Settings
Yet, the landscape of domestic medical practice showed a marked divergence from international guidelines.
Among 70 OB/GYN specialists performing assisted reproductive technology surveyed by NECA, 54.3% reported prescribing Intralipid empirically.
Common reasons cited for prescribing included “expectations of good outcomes” and “the judgment that side effects are relatively minor.” Conversely, doctors who do not prescribe it cited “unclear therapeutic efficacy” as the primary reason. Among 177 patients with a history of treatment, 63.3% stated they chose the injection based on their doctor’s recommendation.
These numbers reflect a reality closer to the fact that clinicians do not necessarily lack awareness of insufficient evidence; rather, the underlying hope that “perhaps it might still help after all” drives actual clinical practice despite that knowledge.
In fertility treatments, such “what-ifs” carry exceptional weight. For patients who have already endured several failed embryo transfers, hearing “the efficacy isn’t certain, but we can try it” resonates far more powerfully than in other medical fields. Driven by anxiety that the next transfer might be their last, patients feel compelled to try everything possible, even if it means incurring extra costs and enduring a few more injections.
The Complexity of Recurrent Failure
Recurrent implantation failure and recurrent miscarriages cannot be explained by a single cause. Chromosomal anomalies and developmental potential of the embryo, uterine cavity structure and endometrial status, endocrine issues like thyroid disorders or diabetes, thrombotic conditions, and parental genetic abnormalities can all intertwine. Immunological causes represent merely one possibility among them.
Concluding that “implantation fails because NK cells are high” or “immunity is too strong and must be lowered” without thoroughly investigating other causes strays far from current medical evidence.
Furthermore, ESHRE does not recommend routine screening for peripheral blood NK cells or uterine NK cells in patients with recurrent implantation failure. Testing methods and normal ranges lack sufficient standardization, and establishing that elevated specific levels directly cause implantation failure remains unproven.
Ultimately, the question posed by NECA’s research is not a simple binary debate over whether “soybean injections should be allowed.” It touches on deeper dilemmas: at what threshold of confirmed probability can a treatment be recommended to patients, and how transparently must medical staff explain uncertainties when offering adjunctive treatments with unclear efficacy?
Dr. Park Dong-ah, Senior Research Fellow at NECA, emphasized, “Although Intralipid injections have been used for a long time in domestic clinical settings, medical evidence and international recommendations remain insufficient.” He stressed the necessity of shared decision-making, where patients are accurately informed in advance about the low level of evidence, potential harms, and costs before jointly deciding whether to proceed with treatment.
The controversy surrounding the ‘soybean injection’ is ultimately not a story about a single bag of milky-white fluid. It raises a critical question for the fertility treatment landscape: When does a ‘treatment with potential’ cross the line into becoming an ‘injection that must inherently be taken’?
The possibility of influencing immune cells differs from increasing pregnancies, and a slight rise in pregnancy rates differs from increasing the birth of healthy children. Bridging that gap is the role of clinical evidence.
That is precisely what Intralipid currently lacks the most.