
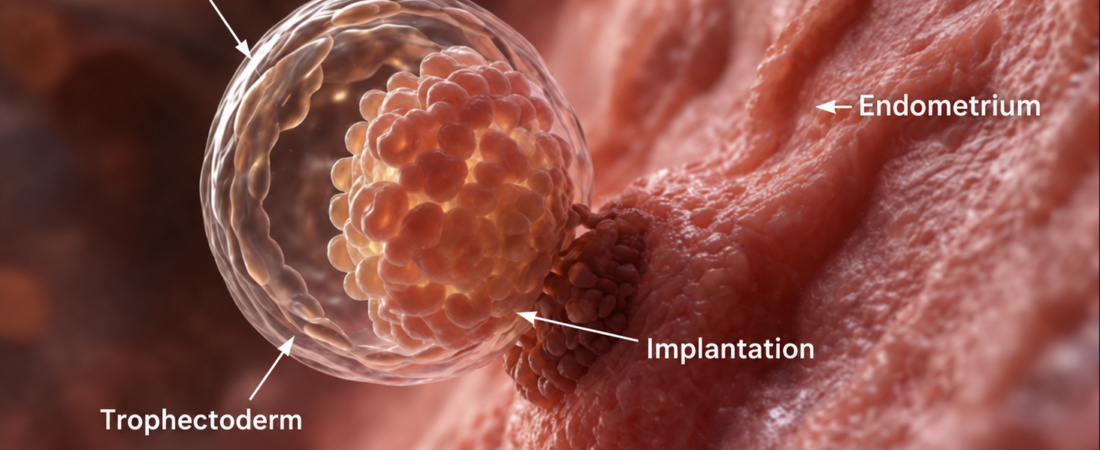
ERA testing aims to personalize embryo-transfer timing by assessing endometrial gene expression. The window of implantation is real biology; routine testing to locate a supposedly displaced window is a separate clinical claim. Randomized evidence has not shown that receptivity-guided timing improves live birth in the population studied.
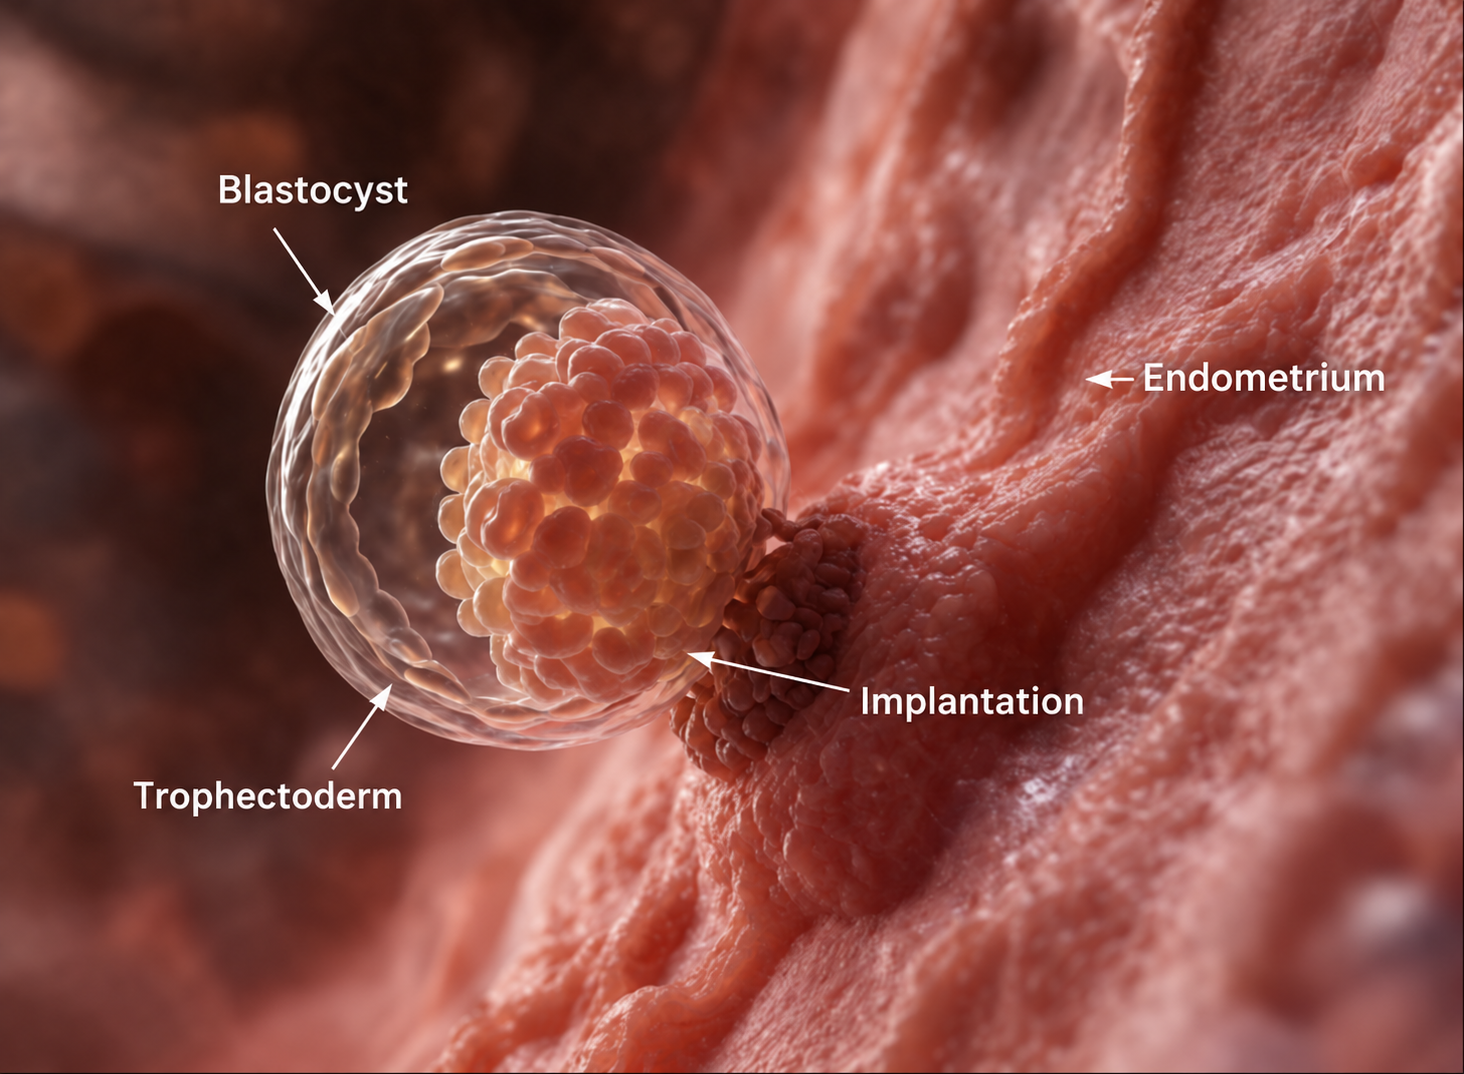
For those undergoing In Vitro Fertilization (IVF), few phrases are as demoralizing as: “The embryo was perfect, but it didn’t implant.” When you have done everything right—optimized your health, stimulated your ovaries, and nurtured your embryos to blastocyst stage—a failed transfer feels less like a biological outcome and more like a mysterious defeat.
However, reproductive medicine is increasingly recognizing that the uterus is not a restaurant open 24/7. It is more like an appointment-only boutique: it only opens its doors for a brief period known as the “Window of Implantation.”
The biological window and the commercial test
Implantation requires coordinated embryo–endometrial development. A test claiming to personalize that timing still needs to demonstrate that using it improves outcomes.
ERA measures gene-expression patterns in an endometrial sample and assigns a receptivity category. The result is not proof that a displaced window caused previous failure.
A biopsy and a personalized label can make the result feel definitive. Test reproducibility, applicability and the consequence of changing timing are separate questions.
What randomized evidence found
A 2022 JAMA trial did not find improved live birth with receptivity-guided timing compared with standard timing in the studied population. This challenges routine use rather than proving every possible subgroup has been settled.
Repeated unsuccessful transfers may justify a structured review of care. They do not by themselves establish that ERA will help; evidence for proposed subgroups remains limited.
- Repeated transfer failure: Review relevant embryo, uterine and protocol factors; ERA is not automatically the next step.
- Unexplained failure: An unknown explanation is not evidence of a displaced implantation window.
- Good-quality embryos: Morphology alone does not establish the cause of failed implantation or prove a benefit from receptivity testing.
The discussion should distinguish clinical pregnancy, ongoing pregnancy and live birth. A change in a test category is not the same as a meaningful reproductive benefit.
Before changing the clock
Ask how the result would change the protocol, what benefit has been shown, and what the biopsy, delay and additional cost involve.
A compelling timing metaphor is not a substitute for outcome data. Good care can include deciding that an extra test is unlikely to add useful information.
Disclaimer: This report is for informational purposes. The ERA test is a specialized diagnostic procedure; discuss its necessity with your reproductive endocrinologist based on your specific treatment history.
The randomized comparison
The JAMA trial compared receptivity-guided and standard timing of frozen embryo transfer. Its findings do not support routine testing in that population; subgroup claims require their own evidence. Original randomized trial: JAMA (2022).
Related reading
"Beyond the Embryo": The Paradigm Shift from Selection to Environment in IVF