
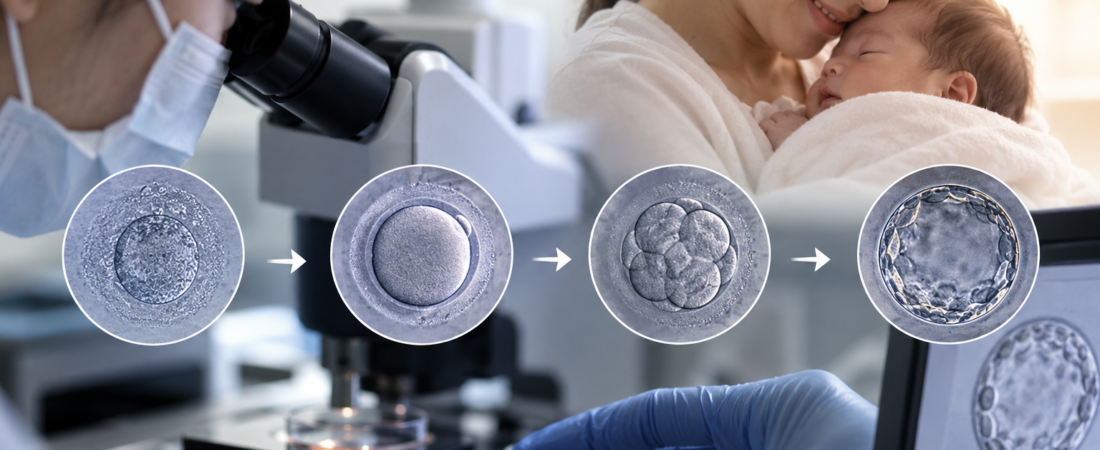

Can immature eggs retrieved during IVF produce additional embryos after rescue in vitro maturation (rescue IVM)? A small retrospective study followed GV oocytes cultured for another 24 hours before ICSI. It reported additional euploid embryos and live births, but lower blastocyst development, selective eligibility and inconsistent figures within the paper require cautious interpretation.
Rescue IVM after unexpectedly poor egg maturation: additional embryos, reported live births and limits of the evidence
- 266 immature oocytes at the germinal vesicle (GV) stage at retrieval cultured further: Nearly half converted into mature (MII) oocytes
- The abstract reports 11 of 47 patients with an additional euploid embryo: The main text reports 13; this unresolved discrepancy is discussed below.
- Reported 20% relative increase in patients with a live birth: A within-cohort comparison, not proof from a randomized trial.
After undergoing egg retrieval, some fertility patients are met with discouraging news: “We retrieved several eggs, but very few of them were mature.”
Not every egg collected during a retrieval cycle is ready for fertilization. In particular, oocytes at the germinal vesicle (GV) stage—where the nuclear envelope remains intact and meiosis is arrested—are immature gametes that have historically been considered unusable in standard In Vitro Fertilization (IVF) and routinely discarded.
However, a study published in the international journal Human Reproduction reveals that instead of giving up on these immature eggs immediately, culturing them for an additional day in the embryology laboratory can provide select patients with new embryos and a renewed chance at live birth.
The research team analyzed 47 women under the age of 39 who underwent Intracytoplasmic Sperm Injection (ICSI) and Preimplantation Genetic Testing for Aneuploidy (PGT-A) between 2017 and 2024 and obtained fewer mature eggs than anticipated.
The study abstract specifies 6 or fewer mature (MII) oocytes, a maturation rate below 80% relative to follicles at least 14 mm at trigger, and 4 or more GV oocytes. Its methods instead say fewer than six MII oocytes, another eligibility wording inconsistency.
Rescue IVM: 127 of 266 GV oocytes matured
In this protocol, oocytes that were already mature (MII) at the time of retrieval were injected via standard ICSI on the day of retrieval. Meanwhile, immature oocytes arrested at the germinal vesicle (GV) stage were cultured in a time-lapse incubator for up to an additional 24 hours.
This technique of culturing eggs that were immature at collection to allow in vitro maturation is known as “rescue in vitro maturation” (rescue IVM).
Across the 47 patients, a total of 266 GV oocytes were identified. Among them, 127 successfully matured within 24 hours to the Metaphase II (MII) stage—the mature stage used for ICSI in this protocol. The maturation rate calculated across all GV oocytes was 47.7%. The paper also reports 53.7% as the mean of individual patient rates; these use different calculations.
On a per-patient average, the number of mature (MII) eggs secured on the day of retrieval was 4.4. However, with the addition of an average of 2.7 mature eggs rescued via IVM, the total number of oocytes available for ICSI increased to an average of 7.1.
For patients who started with few mature eggs, this is by no means an insignificant number.
For a patient with few mature eggs, two or three additional oocytes may matter. Whether they fertilize, become blastocysts and produce transferable embryos could influence later treatment options. This study does not establish that rescue IVM prevents another stimulation or retrieval cycle.
Blastocyst development and PGT-A results
However, oocytes matured through rescue IVM did not display identical developmental competence to those that were mature in vivo from the start.
While the fertilization rate of rescue IVM oocytes did not differ significantly from baseline MII oocytes, their rate of progression to the blastocyst stage was relatively lower.
In other words: culturing immature eggs allows a substantial portion to achieve nuclear maturation, but not all of those rescued eggs will develop into viable embryos.
Yet, once an embryo successfully cleared the hurdle of reaching the blastocyst stage, the clinical picture changed.
Blastocyst morphology and the pooled proportion classified as euploid by PGT-A did not differ significantly between groups. This is not proof of equivalence or a guarantee of a healthy child. The unpaired patient-level euploidy analysis was significant (P = 0.04), while the paired analysis was not.
Reaching the blastocyst stage was an important limitation, but the study did not establish it as the only biological barrier or resolve long-term offspring outcomes.
Additional euploid embryos: interpreting the patient counts
The most striking finding was the actual acquisition of transferable euploid embryos.
The abstract reports 11 of 47 women with at least one additional euploid embryo from rescue IVM. The results and Table 3 instead classify 13 women as obtaining a rescued euploid blastocyst. This inconsistency remains unresolved; neither count should be treated as a precise benefit estimate without clarification.
Gametes that would have been labeled immature and discarded on the day of retrieval successfully traversed extended culture, microinjection, embryonic cleavage, blastocyst biopsy, and PGT-A to become embryos classified as euploid by PGT-A and available for transfer.
From a patient’s standpoint, this represents far more than just “saving one more immature egg.”
In this study, only embryos classified as euploid were transferred after blastocyst biopsy and PGT-A. Attrition occurs throughout maturation, fertilization and embryo development. This protocol does not mean PGT-A is required for every rescue IVM cycle; the authors explicitly state that its usual IVF indications should apply.
Reported live births: what a 20% relative increase means
The authors compared outcomes within the same cohort with and without including embryos derived from rescue IVM. This was not a randomized comparison with a separate group whose GV oocytes were discarded.
The abstract reports an 8% relative increase in patients with a euploid embryo. However, the results report 26 to 30 patients, approximately 15%; the 8% figure corresponds to 36 to 39 patients obtaining any blastocyst. The article reports both versions because the source is internally inconsistent.
Patients reported as achieving at least one live birth increased from 15 to 18 when rescue-derived embryos were included: a 20% relative increase.
This is not a 20 percentage point increase or proof that every patient gains a 20% better chance. The methods define their live-birth endpoint as an ongoing pregnancy beyond 22 weeks, although newborn outcomes are also reported. Larger studies and longer follow-up are needed to establish effectiveness and offspring safety.
Who was studied and what remains uncertain
The investigators were careful to establish boundaries around interpreting these results.
This was a single-center retrospective study involving a modest sample size of 47 women. Crucially, the protocol was not applied indiscriminately to all IVF patients, but to a carefully defined subpopulation: women under 39 who experienced unexpectedly poor oocyte maturation and had four or more GV oocytes available.
Consequently, it is difficult to generalize these findings to claim that rescue IVM will universally raise pregnancy or birth rates for every IVF cycle.
Furthermore, the lower blastocyst conversion rate observed in in vitro matured eggs remains an acknowledged biological limitation.
Nevertheless, the central takeaway of this study is unmistakable: a diagnosis of “immature” on the day of retrieval does not mean the egg’s biological potential ends there.
Every oocyte may matter when mature eggs are scarce. However, these selected patients had unexpectedly low maturation, and the authors describe generally normal baseline reserve measures. The findings do not establish rescue IVM as a proven strategy for all patients with diminished ovarian reserve or repeatedly low egg yield.
Moving forward, reproductive medicine will need refined predictive models to determine which patients’ GV oocytes are most likely to mature and which eggs may produce transferable embryos and live births, alongside adequate assessment of offspring health.
“Should we discard immature eggs, or wait one more day?” For fertility patients facing a scarcity of eggs, a single extra day in the embryology incubator may be more than passive waiting—it could be the window that creates a euploid embryo and another opportunity to hold a child.
For context on chromosome screening, see PGT-A in IVF: live birth and pregnancy loss outcomes. Obtaining an embryo classified as euploid and demonstrating a treatment benefit are different questions.
Medical Source & Study Reference
- Journal: Human Reproduction (Official Journal of the European Society of Human Reproduction and Embryology, ESHRE), Vol. 41, Issue 9, pp. 1507–1521 (September 2026).
- Study Title: Germinal vesicle oocytes’ rescue: a worthless treatment or a patient-centred approach? Eight years of clinical experience in poor prognosis patients
- Lead Authors: Danilo Cimadomo et al.
- DOI: 10.1093/humrep/deag115 | Article ID: deag115
※ This article was synthesized based on the 8-year clinical study published in Human Reproduction (September 2026). It does not replace individualized clinical diagnosis or medical care, and specific embryological decisions should always be made in consultation with a qualified reproductive endocrinologist and clinical embryologist.
※ The images associated with this article were generated using generative AI (ChatGPT, OpenAI) as illustrative visual references and do not depict real individuals.